Denial codes can be a significant obstacle to successful reimbursement, and stands in the way of the
practice’s revenue. A survey conducted by Experian Health in 2024, indicates that 84% of healthcare
providers wish to cut down their claim denials and have kept it at the top of their to-do list. From
this it is clear that minimizing denials isn’t just a goal, it’s a major priority for most
organizations. This can be achieved with a clear understanding of the denial remark codes and proactive
steps that speeds up the entire process of revenue cycle.
What is a denied claim?
A denied claim is the one for which the Insurance Company refuses to make payment after it has been
processed and reviewed since it doesn’t meet their payment criteria. It can be due to many reasons such
as coding errors, missing documentation, lack of medical necessity, or policy exclusions.
Every payer will send an Explanation of Benefits (EOB) or Electronic Remittance Advice (ERA) that
explains why the claim was denied. Even though the claim is denied by the payer we can appeal for it
after identifying the reason for denial and correcting it.
In this blog let’s discuss on the common denial remark codes and suggestions on how to rectify them.
They are the standardized alphanumeric codes used by insurance companies to explain why a claim was
denied or adjusted. In practice, it could mean the CARC, the RARC, or a combination of both.
The revenue cycle is the full process from patient registration to final payment. Denials can halt this
cycle multiple times, leading to delays in reimbursement. Understanding these codes helps us to respond
appropriately to the denied or rejected claims. It provides the clarity, needed for re-appeals and boost
the revenue cycle efficiency.
What is CARC & RARC?
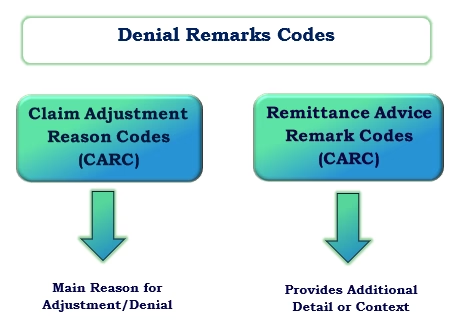
Claim Adjustment Reason Codes (CARCs) and Remittance Advice Remark Codes (RARCs) are the specific codes
that point out the category of the problem and tells what went wrong exactly.
CARC tells why a claim or service was adjusted or denied. For example, CARC
27 means “Expenses incurred after coverage terminated.”
RARC add extra context or clarification to a CARC. For instance, alongside CARC
27, a RARC N290 means a “Missing or incomplete/invalid patient insured
identifier.” It provides a more descriptive detail.
What are the main CARC Code
Categories?
CARC explains why a claim
or part of a claim was adjusted or denied. They are often paired with a two-character codes that
assign financial responsibility for an adjustment on a medical claim. The common types are CO
(Contractual Obligation), OA (Other Adjustment), PI (Payer Initiated Reduction), PR (Patient
Responsibility) and CR (Correction and Reversal).
CO
CO – Contractual Obligation
These are adjustments due to an agreement between the provider and the payer and cannot bill the
patient for it. For example, if the billed charge is $150 and allowed amount as per the agreement is
$100 the provider writes off the exceeded difference amount.
OA
OA – Other Adjustment
Adjustments that don’t fall under contractual obligations or patient responsibility, such as
corrections or policy changes. For Example, Claim paid under a different benefit plan, or system
correction, the payer reprocessed a claim due to an internal error such amounts are adjusted as OA.
PR
PR – Patient Responsibility
Patients are responsible for paying this amount, such as copays, coinsurance, or deductibles. PR codes
clearly show what you can bill the patient directly.
Example: Patient has a $30 copay or $200 deductible that hasn’t been met.
PI
PI – Payer Initiated Reductions
Reductions in payment when the payer reduces the payment for reasons such as medical necessity,
bundling, or coding edits.
CR
CR – Correction and Reversal
Used when reversing a previous adjustment or correcting a prior transaction.
What are the uses of these CARC Group codes?
These codes help to determine the appropriate action to be taken on a denial, such as whether to bill
the patient, appeal the payer’s decision, or simply write off the amount. Correct interpretation
prevents billing errors and compliance issues.
The top 10 Denial Codes in
Medical Billing
Let us discuss the most commonly occurring denials and their remark codes under each category and
solutions to rectify them.
This claim denial code is used to intimate that the service was rendered after the patient
insurance policy’s termination. These types of denials have to be prevented because they’re hard to
fight. This implies verifying the patients’ insurance benefits before the services are rendered, so
that we can know about their insurance coverage status. Advice the front office staff to verify
insurance status for every visit. This helps get the most up-to-date insurance information or
determine whether the individual is a self-pay patient, enabling to collect payment at the time of
service.
Actionable Solution: Implement mandatory real-time eligibility checks at
patient intake before service delivery.
This refers to any claim charges made while the patient was suffering from an interruption of their
insurance coverage. To rectify this remark code, the medical practice should verify that the
patient's insurance is current, and resubmit all claims being denied as a result of this lapse in
coverage. It is important that practices stay up to date on insurance verifications, so as to avoid
losses due to denials. Staying organized and documenting all patient interaction, helps practices
quickly and efficiently identify any issues related to insurance lapses or other denied claims. This
allows them to mitigate potential losses and ensure timely payment processing.
Actionable Solution: Re-verify effective coverage dates and document
interactions to dispute erroneous lapse claims.
This denied code is used when the payers couldn’t find the patient in its system under the given
subscriber details. This may occur due to simple data entry errors or outdated information like typo
or discrepancy in the patient's name, date of birth, or address on the claim compared to the
information on file with the insurance company. It might also occur due to wrong submission of the
claim to another insurance company that does not cover the patient at all. Always double-check the
patient's demographic details and provide the exact information as appearing on their insurance
card. Check with the payer for any discrepancies in their system and rectify it. Reach out to the
patient to get the accurate, current information and update their records and resubmit the claim
with the corrected information.
Actionable Solution: Validate patient demographic match against insurance card
copy and resubmit with verified subscriber ID.
Category 2
Under Authorization Category
Getting a pre-authorization is one of the most important steps in the billing process. Each payer
has their rules or guidelines that requires getting a prior permission before offering the services
for some cases like high-cost diagnostics tests or surgeries. Without proper prior-authorization the
claims will not be processed and will be denied or rejected.
This code is used when the payer requires prior authorization (PA) for a service or procedure, but
no valid authorization is found in their system at the time of claim review. The various reasons for
that can be:
- Have not obtained the Prior authorization before service was rendered.
- Authorization request was denied but service was still provided.
- Authorization was obtained, but for the wrong CPT code or diagnosis.
- Authorization expired before the date of service.
Always check with payer to confirm if the service requires prior authorization. If authorization
exists, verify that the auth number matches. If no PA was obtained, request a retro-authorization
(however only some payers allow this within a certain timeframe).
Actionable Solution: Request retro-authorization immediately if permitted by
payer guidelines, or append verified auth numbers.
This is similar to PR 243 but under this we cannot bill the patient for the denied amount, it’s the
provider’s responsibility. This happens when the provider has a contractual agreement with the payer
to follow certain authorization rules.
Compliance Advisory: Contractual Obligation (CO) precludes billing the
patient. Prior auth protocols must be audited to avoid mandatory write-offs.
Category 3
Coding Denials
Coding errors or missing modifiers is the major reason for claim rejection/denial. Always ensure to
use the correct diagnosis code with relevant CPT codes and appropriate modifiers.
It indicates the wrong usage of modifiers with the CPT/HCPCS codes. Include modifiers wherever
necessary (e.g., -25 for significant, separately identifiable E/M services also verify the modifier
alignment with the procedure code according to CPT guidelines and payer policy. Use official CMS Modifier Guidelines to confirm correct usage. If a modifier is
missing append it and resubmit the claim.
Actionable Solution: Verify CPT-modifier compatibility (e.g., -25, -59, -76)
and resubmit with appropriate modifier attachment.
This is essentially a “medical necessity denial” and is reported when the diagnosis code submitted
doesn’t justify the medical necessity of the service according to the payer’s coverage policy.
Choose procedure codes that match the service provided.
We at Shoreline Medical Billing company recognize how much accurate billing impacts both provider
revenue and patient confidence. Our team of certified experts ensure to give error-free claims on
the very first submission, reducing the rate of denials.
Actionable Solution: Re-examine medical documentation to map specific,
billable ICD-10 codes supporting medical necessity.
Category 4
Documentation Denial Code
Incomplete documentation creates immediate payment friction. Comprehensive clinical record
attachments eliminate these preventable denials.
It means that the attached document is not sufficient to process the claim and needs extra details.
Check whether the chief complaint and history of present illness are clearly documented and provided
with supporting details. Gather complete and clear documentation from the medical record. Re submit
the claim with corrected and complete documentation. For future claims, use a documentation
checklist before submission.
Actionable Solution: Compile complete clinical records (HPI, exam notes,
diagnostic findings) and submit via secure electronic attachment.
Category 5
Other Denial Codes
Operational bottlenecks like duplicate submissions and missed timely filing windows require
proactive automated scrubbing.
This code means the claim was denied because the payer believes the same service was already
submitted for the same patient, date, and provider. This may be due to:
- The same claim was submitted twice (manually or electronically).
- Overlapping service dates for identical CPT codes.
- Modifier missing when billing for separate but similar services.
Verify if the service was already paid. If it’s a legitimate second service, add the correct
modifier (e.g., -59, -76) and resubmit with an explanation.
Actionable Solution: Append modifier -59 or -76 if billing distinct services,
or withdraw redundant duplicate claims.
This denial occurs when the claim was submitted after the payer’s filing deadline. Implement
internal claim tracking team to check payer’s timely filing policy and submit within limits.
Actionable Solution: Maintain automated filing ticklers and submit
clearinghouse timestamp proof if timely filing was met.
OA-27
Coverage Terminated
PR-200
Lapse in Coverage
PR-31
Patient Not Found
PR-243
Not Authorized
CO-197
No Pre-Auth
CO-4
Modifier Error
CO-11
Inconsistent Dx
CO-251
Incomplete Docs
CO-18
Duplicate Claim
CO-29
Filing Expired
Denial Prevention Guarantee
Turn Denials into Paid Claims with Shoreline RCM
Our certified billing and denial management specialists resolve complex CARC
& RARC codes, scrub claims pre-submission, and recover uncollected revenue for your practice.